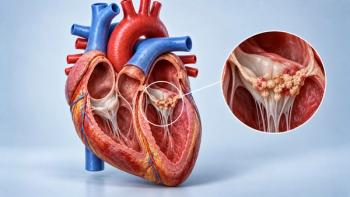
For women, Boccara advocated for greater emphasis on their risk of heart disease, as data indicates they are losing their protection against CVD before the beginning of menopause. In counseling women living with HIV, pharmacists have a responsibility to educate them on their particularly increased CVD risk and steps they can take to reduce their risk.1
These steps can include statins, which are effective at treating dyslipidemia and reducing CVD risk. In one study, Grinspoon et al solidified the efficacy of pitavastatin (Livalo; Kowa Pharmaceuticals) in reducing the risk of a major adverse cardiovascular event in participants with HIV infection compared with placebo. Boccara told the audience that pharmacists and providers should ensure they adhere to guidance on the prescription of statin therapy in primary CVD prevention in PLWH, which often recommend the use of multiple drugs.3
Boccara also touched on the ongoing debate surrounding whether individuals with HIV have higher prevalence of hypertension, which he noted varies worldwide depending on the incidence of obesity, diabetes, or existence of poor social conditions. Regardless of the supposed risk, Boccara endorsed the use of cardiovascular risk scores in PLWH, such as the Systematic Coronary Risk Evaluation 2 (SCORE2) guidelines in Europe or ASCVD score in the US. He also advocated for the development of risk scores for patients in sub-Saharan Africa and Asia, who are at heightened risk of developing HIV.1
Viral Hepatitis Presents Unique Risk to PLWH
Viral hepatitis—whether in the form of hepatitis C virus (HCV), hepatitis B virus (HBV), or hepatitis delta virus (HDV)—presents a major concern for PLWH, according to Nunes. He explained to the session that the existence of many overlapping modes of transmission makes diagnosis and treatment difficult for patients in this population. Management and diagnosis are especially difficult for key subgroups, including men who have sex with men, prison inmates, and individuals who inject drugs, necessitating targeted support for these demographics.1
Surprisingly—and a helpful development for pharmacists—guideline recommendations support the same strategies for treatment and retreatment of HCV in PLWH and those without HIV. Using the same recommendations for patients without HIV allows for easier coordination of care and more seamless transitions if a patient develops HIV and viral hepatitis and suddenly requires specialized care.1
Improvements in diagnosis are paramount to tackling the overall burden of viral hepatitis. Nunes emphasized that, although cure rates of viral hepatitis are high, reinfection can occur. A systematic review of 41 studies found a significant risk of reinfection in PLWH, especially in men who have sex with men. To better diagnose patients with viral hepatitis and prevent spread, Nunes advocated for “moving to new strategies using tools already available to us, like point-of-care testing.”1
Patients using ART may have enhanced difficulty at achieving a functional cure to viral hepatitis, especially HBV. This is why, according to Nunes, vaccination is critical, especially providing it to nonimmune, non-HBV patients with HIV to prevent infection.1
Healthy Aging is Critical to Ensuring Quality of Life
As previously mentioned, the world’s population is steadily increasing in age. This trend is similar for patients contracting HIV, according to Wong; currently, 40 million individuals live with HIV worldwide, and among these, almost 10 million are aged 50 years or older. Furthermore, by 2030, the proportion of aging among PLWH are set to increase across geographic regions and gender. This reality necessitates an evaluation of the burdens that PLWH may experience as their treatment allows for longer lifespans.1
In 1996—before the widespread use of ART—life expectancy for PLWH was substantially lower compared with the general population. This life expectancy is vastly increased, with the differences between PLWH and the general population significantly reduced; however, as Wong posed to the audience, it remains to be seen if an increase in life expectancy is in conjunction with a positive quality of life for PLWH.1
Wong explained that people aging with HIV can experience accelerated or accentuated aging, which is characterized by differences in chronological versus biological age; increases in multimorbidity, which is the experience of developing 2 or more comorbidities; and increases in the development of geriatric syndromes, including instability, immobility, sarcopenia, and frailty, all of which are more prevalent in PLWH. Continuing a trend observed throughout the session, these risks—especially cognitive impairment and falls—are observed more frequently in women compared with men.1
Buoyed by the concept of “healthy aging”—which the World Health Organization defines as “being able to be and to do what patients have reason to value throughout their lives—Wong advocated for leveraging available tools and using research opportunities to heighten the ability for PLWH to age properly. Specifically, Wong explained the importance of maintaining a patient’s functional ability, which requires reconciling the intrinsic capacity of patients (cognition, mobility, vitality, and psychological concerns) with their external environments (economy, resources, social norms, and values).1
By enabling healthy aging, PLWH will have the opportunity to not only live longer, but live more thoroughly and thoughtfully.1
REFERENCES
1. Waters L, Baber T, Chandiwana N, et al. HIV clinical challenges. Presented: 13th IAS Conference on HIV Science. July 13-17, 2025. Nairobi, Kenya. Accessed via Virtual Platform on July 21, 2025. https://conference.ias2025.org/media-1230-hiv-clinical-challenges
2. Sarkar S, Brown TB. CROI 2024: Metabolic and other complications of HIV infection. Top Antivir Med. 2024;32(3):504-510. PMID:39142292. Published July 17, 2024. Accessed July 21, 2025. https://pubmed.ncbi.nlm.nih.gov/39142292/
3. Grinspoon SK, Fitch KV, Zanni MV, et al. Pitavastatin to prevent cardiovascular disease in HIV infection. N Engl J Med. 2023;389(8):687-699. doi:10.1056/NEJMoa2304146