A randomized clinical trial found that dedicated oncology pharmacist care reduced adverse drug reactions among patients with hematologic malignancies.
Rusfertide gives adults with polycythemia vera a first-in-class option to cut phlebotomy dependence and control hematocrit.
The FDA approved rusfertide (Mimrylo; Takeda Pharmaceuticals America, Inc), the first hepcidin-mimetic therapy for adults with polycythemia vera (PV) whose disease is not adequately controlled with existing treatments.
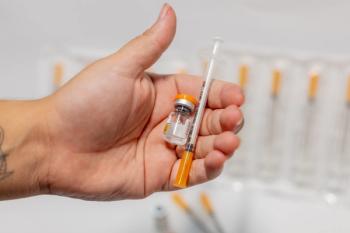
For pharmacists, the approval introduces a subcutaneous, self-injected agent that meaningfully reduces the need for therapeutic phlebotomy, a longstanding treatment burden, while improving hematocrit control in a disease defined by red blood cell overproduction and elevated cardiovascular risk.1
PV is a chronic myeloproliferative disorder in which the body overproduces red blood cells, thickening the blood and raising the risk of blood clots, stroke, and heart attack. A central goal of management is keeping hematocrit, the proportion of red blood cells in the blood, below 45% to reduce those cardiovascular risks, which often requires repeated phlebotomy.
Rusfertide is a first-in-class peptide that mimics hepcidin, the hormone that naturally regulates iron in the body. By limiting the iron available for the production of new red blood cells, rusfertide curbs their overproduction and helps keep red blood cell levels under control.1,2
“We know that regular phlebotomy is time-consuming, ties patients to the health care system, can be poorly tolerated, and—from real-world studies—often fails to consistently control hematocrit at goal levels,” Andrew Kuykendall, MD, study investigator and a hematologist-oncologist and associate member at Moffitt Cancer Center in the Department of Malignant Hematology, told Pharmacy Times. “Rusfertide offers an alternative that can be self-administered at home, is reasonably well tolerated, and consistently maintains hematocrit at goal levels.”
The approval was supported by data from VERIFY (NCT05210790), a multicenter, randomized, double-blind, placebo-controlled phase 3 study of 293 adults with PV who required frequent phlebotomies despite ongoing standard-of-care therapy. Patients (median age, 57 years; 73.0% male) were randomly assigned 1:1 to rusfertide or placebo over 32 weeks. Rusfertide began at 19 mg administered subcutaneously once weekly and was titrated to maintain hematocrit below 45%. Roughly 56% of patients in each arm received concurrent cytoreductive therapy.1-3
Regarding the primary end point, 76.9% of patients receiving rusfertide required no phlebotomies and did not meet phlebotomy eligibility criteria between weeks 20 and 32, compared with 32.9% receiving placebo (P < .0001). The mean number of phlebotomies across weeks 0 to 32 was 0.5 with rusfertide vs 1.8 with placebo (P < .0001), and more patients maintained hematocrit below 45% (62.6% vs 14.4%; P < .0001). Patients receiving rusfertide also showed statistically significant improvements in patient-reported fatigue on the Patient-Reported Outcomes Measurement Information System Fatigue SF-8a and the Myelofibrosis Symptom Assessment Form Total Symptom Score questionnaires (P < .03).3
The most common adverse reactions were injection-site reactions and anemia; in VERIFY Part 1a, injection-site reactions occurred in 55.9% of the rusfertide group and 32.9% of the placebo group, and anemia occurred in 15.9% vs 4.1%. Serious adverse events occurred in 3.4% of patients receiving rusfertide and in 4.8% receiving placebo, none of which were considered related to rusfertide.1,3
“Rusfertide does not obviate the benefits of cytoreductive therapy but can be used in conjunction with cytoreductive therapy when needed, as evidenced by the fact that around half of patients on the VERIFY study continued their standard of care cytoreductive agents,” Kuykendall said. “In patients who are solely receiving cytoreductive therapy to avoid phlebotomies, rusfertide could be an alternative. Additionally, it could allow for more optimal dosing of cytoreductive therapies that often have adverse effects at higher dose levels.”
Because rusfertide is self-injected, pharmacists have a direct role in counseling patients on subcutaneous injection technique, site rotation to mitigate injection site reactions, and recognizing signs of anemia given the drug’s iron-restricting mechanism. Adherence support and reinforcing the ongoing need for hematocrit monitoring during titration are also relevant touchpoints.